
Beyond Affirmation: The Neurobiology of LGBTQ Minority Stress and Trauma

Updated: Sep 21
By Dr. Maria Niitepold, PsyD | Licensed Psychologist | EMDR, Brainspotting & CRM

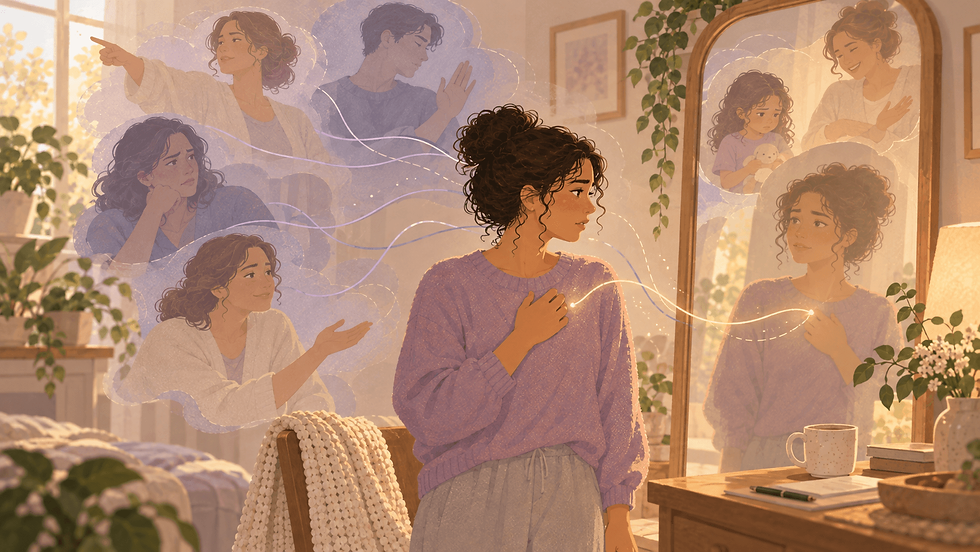
You did the scan before you got out of the car. You probably did not even notice yourself doing it. The parking lot. The bumper stickers. The people near the entrance. A read of the room before the room, done in under three seconds, by a system that has been running this check for so long it no longer files a report.
Inside, at the coffee shop, your partner reaches for your hand, and something in you does the math before your fingers decide. Who is here. What town this is. Whether today is a day the math comes out in your favor. Maybe you take the hand. Maybe you find a reason to need both of yours. Either way, something got spent.
If you are LGBTQ, there is a good chance nobody ever taught you to call any of this stress, because it is just how you move through the world. It is ambient. It is procedural. It is also, neurobiologically, one of the most expensive programs a nervous system can run, and it has been running yours for years.
This post is about what that program actually costs, why a rainbow flag in a therapist's window does not turn it off, and what kind of work reaches the level where the vigilance actually lives.
Quick Answer: What Is LGBTQ Minority Stress?
Minority stress is the chronic load carried by people with stigmatized identities: the scanning, the concealment decisions, the internalized messages, and the bracing that run underneath ordinary life. It is not one event but thousands of small expenditures, and it measurably dysregulates the nervous system. Affirming therapy validates it. Somatic trauma therapy releases it.
Table of Contents
What Minority Stress Actually Is
The clinical framework comes from researcher Ilan Meyer, and it names something LGBTQ adults have always known without the vocabulary: that living with a stigmatized identity produces a distinct, chronic layer of stress that other people simply do not carry.
The model distinguishes two sources. Distal stressors are the external events: the discrimination, the rejection, the legislation, the comment at the family table, the thing that happened in the school hallway. Proximal stressors are what the external environment installs internally: the vigilance, the concealment calculus, the expectation of rejection, the internalized versions of the messages you grew up marinating in.
Here is the part that matters clinically. The distal events may be occasional. The proximal machinery runs continuously. You do not have to be actively discriminated against on a Tuesday for your system to spend Tuesday scanning for it. The threat does not have to arrive for the threat-detection to bill you.
That is why minority stress does not behave like ordinary stress, which spikes and resolves. It behaves like a load: cumulative, ambient, and largely invisible to the person carrying it, because there was never a version of life without it to compare against.
The Hypervigilance You Stopped Noticing
Every nervous system scans for threat. Yours has been trained to scan for a specific kind, in a specific set of environments, with a thoroughness that most people around you have never needed to develop.
The new workplace, read for safety before you read it for anything else. The doctor's office, and the split-second decision about the pronoun on the intake form. The rental car counter in an unfamiliar county. The hotel check-in with your partner. The moment a conversation at work drifts toward weekends, and you feel yourself go slightly more managed.
None of this registers as fear anymore. It registers as normal. That is precisely the problem, because the amygdala does not care whether you have renamed the program. It is still running a threat-detection protocol, still spending cortisol and adrenaline on rooms that mostly turn out fine, still holding the body at a low idle of readiness that never fully releases.
This is the same architecture I map in why high-achievers live outside their window of tolerance: a nervous system that has narrowed its range of felt safety and now spends most of its life above the line, mistaking chronic activation for personality. The exhaustion this produces is not laziness and it is not depression, though it can shade into both. It is the predictable output of a security system that has never once been fully off duty.
Concealment: The Cost of Editing Yourself
Concealment is usually discussed as a choice: to be out or not, here or there, with them or not with them. Neurobiologically, it is better understood as a workload. Every environment where some portion of you is edited requires continuous, real-time cognitive labor. Tracking what this version of you has said. Managing pronouns, names, and stories. Steering conversations away from the weekend, the partner, the past. Reading each new person for how much of you their presence can hold.
Researchers who study concealment describe exactly this: the self-monitoring is itself a chronic stressor, independent of whether anyone ever finds out. The secret does not have to be discovered to be expensive. It is expensive to carry.
Many LGBTQ professionals become extraordinarily good at this editing, so good it looks like social skill, and in a sense it is. It is also a version of the pattern I map in the fawn response and the professional cost of chronic accommodation: safety purchased through performance, one managed interaction at a time.
For those who carry more than one marginalized identity, the workload compounds. Race, disability, class, and religion each add tracks to the tape the system has to manage. Being an immigrant or first-generation American layers its own version of code-switching on top, the belonging-everywhere-and-nowhere pattern that people who grew up across cultures know in their bones.
And underneath the workload sits the deeper cost: a body that has learned that being fully seen is a risk, the exact wiring I take apart in why the fear of being seen makes visibility feel unsafe. The editing was protective. It also taught your nervous system that the unedited you is a liability.
Internalized Messages: When the Outside Got In
The messages arrived before your defenses did. The sermon you sat through at fourteen. The joke at the dinner table that everyone laughed at, including you, because what else do you do. The word in the hallway. The silence, in your family, around an entire category of human life, which is its own kind of message.
Internalized homophobia and transphobia are not character flaws, and they are not evidence that you have failed at self-acceptance. They are what happens when the outside got in early, before you had any framework to argue with it, and set up residence at a level that argument does not reach. For those raised inside high-control religion, this carries a clinical name, religious trauma, and its grip routinely outlasts the beliefs themselves by decades.
This is why so many LGBTQ adults live with a strange split. The thinking mind is fully affirming, articulate, sometimes professionally fluent in this exact subject. And the body still flinches at a hymn. Still braces during intimacy. Still runs a shame response that the intellect rejected fifteen years ago.
You have not failed to do the work. The work you did reached the part of you that thinks. The imprint lives in the part that reacts. Understanding and healing, it turns out, have different addresses.
If the scanning, the editing, and the bracing have been running so long they feel like personality, they are not. They are a nervous system doing exactly what chronic minority stress trains it to do. The training can be undone at the level where it was installed. I offer EMDR, Brainspotting, and CRM for LGBTQ adults, in person in Gulf Breeze, Florida and online across New York and Florida and throughout all PsyPact states. You can request a 15-minute consultation whenever you are ready.
Why Affirming Isn't the Same as Trauma-Informed
Affirming therapy means your identity will not be pathologized, your language will be used, and your experience will not be put on trial. That is the floor. It is necessary, it is non-negotiable, and it is the baseline I hold in my LGBTQ affirming therapy practice. It is also not the same thing as trauma competence.
Many LGBTQ adults spend years in genuinely affirming therapy and reach a quiet plateau. They feel understood. They feel respected. And the vigilance, the shame, the reactivity in close relationships, do not move.
That plateau is not a failure, yours or the therapist's. It is the boundary between validation and repair. Validation is cognitive and relational. The load is physiological.
A trauma-informed clinician works with the nervous system underneath the identity content: the pacing, the consent, the body signals, the whole architecture I lay out in how trauma-informed therapists approach therapy differently. For LGBTQ clients specifically, that means treating the scanning, the concealment fatigue, and the internalized residue as trauma physiology to be processed, not merely as experiences to be affirmed.
One is a safe room. The other is what happens in it.
The Body Keeps the Minority Stress
The cumulative wear of a system that never idles has a clinical name: allostatic load. It is the physiological bill for years of adaptation, and it comes due in the body.
The fatigue that sleep does not fix, because the night shift never actually ends. The gut that runs tight. The jaw. The shoulders that live an inch high. The startle response that fires at a slammed door, a certain tone of voice, a headline. The immune system that seems perpetually a little worn down.
And, for many, the strategic absence: the numbness, the flatness, the practiced ability to leave the room without leaving the chair. Checking out was a brilliant solution once, at the dinner table, in the pew, in the locker room, and the hiding, avoiding, submitting, and dissociating responses that got you through are a family with a shared logic. At the far end of that family sits full disconnection, dissociation itself, which for many LGBTQ adults was simply how childhood was survivable.
None of this is weakness. All of it is expenditure. The body has been paying for the vigilance the whole time, and the symptoms are the receipts.
How Somatic Therapy Approaches This Differently
Talk therapy engages the prefrontal cortex, the part of you that already knows your fear is often evidence-based and your identity is not a problem. Minority stress does not live there. It lives in the subcortical systems that decide, before thought arrives, whether the room is safe, whether the hand can be taken, whether the real answer can be given. Reaching that level is the whole reason somatic therapy enters where talk therapy stalls.
EMDR processes the accumulated record. Not just the big events, if there were big events, but the thousand small ones: the hallway, the sermon, the meeting, the moments the system filed as threat and never got to close. Bilateral stimulation lets the brain finally metabolize what it could only store at the time, and the present-day cues that used to fire the old response gradually stop carrying the charge.
And when the load is heavy or the numbness is thick, processing is not where we start. We start by building internal safety first, which is exactly how the Comprehensive Resource Model makes trauma therapy safe for systems that learned early that the world would not provide it. CRM builds the resource the environment never reliably offered: an internal, body-level experience of being accompanied and steady, so that your safety stops depending on the political weather, the region, or the room.
None of this requires you to re-narrate what happened, or to perform your history for a stranger. The work happens below the story, at the level of the imprint, at a pace your system sets.
What Healing Actually Looks Like
Not the erasure of good judgment. You will still read rooms, and in some rooms that reading will still be warranted. Discernment stays. What changes is the default. The scan becomes a tool you pick up when context calls for it, instead of a program that runs on every room, every stranger, every Tuesday.
Clients describe it in small, specific ways. Taking the hand without doing the math first. Answering the weekend question with the actual weekend. Noticing, mid-afternoon, an unfamiliar quiet in the chest and realizing it is the absence of bracing. Sleeping like someone whose night shift finally ended.
The internalized voice loses volume, not because you out-argued it, but because the material underneath it got processed. The flinch at the hymn softens into just a song. Joy stops arriving with a bodyguard.
And the energy that vigilance was consuming, which was enormous, comes back online for the life it was always meant to fund: the work, the love, the ordinary unguarded days.
Checklist: Is Minority Stress Running in Your Nervous System?
Read slowly. Notice what your body does with each one.
You scan new environments for identity-safety automatically, and you cannot remember learning to.
You maintain different versions of yourself for different settings, and switching between them is effortful even when it is skillful.
You feel a physical response, adrenaline, tightening, dread, to certain signs, headlines, or conversations before any thought forms.
You are more tired than your life seems to explain, and rest does not fully repair it.
Your thinking is fully affirming and some part of your body still is not.
Intimacy, visibility, or being celebrated can trigger bracing instead of ease.
You have a practiced ability to go somewhere else internally while remaining pleasant externally.
You did years of therapy that helped you feel understood and left the vigilance untouched.
If most of these land, what you are carrying has a name, a mechanism, and a treatment. It is not your personality. It is your protection, and protection can finally be allowed to stand down.
Frequently Asked Questions
What is minority stress and how does it affect mental health?
Minority stress is the chronic, cumulative stress carried by people with stigmatized identities, first formalized by researcher Ilan Meyer. It includes external events like discrimination and rejection, and the internal machinery those events install: hypervigilance, concealment labor, expectation of rejection, and internalized stigma. Because the internal layer runs continuously, minority stress behaves like a load rather than an event, and it correlates consistently with elevated anxiety, depression, sleep disruption, and stress-related physical symptoms. It is a nervous system effect, not a character trait, and it responds to nervous-system-level treatment.
Is the constant scanning actually a trauma response?
Functionally, yes. Hypervigilance is a threat-detection adaptation, and a nervous system that has learned through real experience that certain environments carry identity-based risk will run that detection automatically. The scanning is often evidence-based rather than irrational, which is exactly why cognitive approaches that treat it as a distortion tend to fail. The clinical goal is not to delete discernment. It is to return the scan to voluntary use instead of a permanent default.
Why do I still feel shame when I'm fully out and self-accepting?
Because acceptance happened in the thinking brain and the shame was installed below it, usually years earlier, before you had any framework to refuse the messages. Internalized stigma is stored as somatic imprint, not as an opinion, which is why it does not respond to better arguments. The split you feel, an affirming mind and a flinching body, is one of the most common presentations in LGBTQ trauma work, and it is precisely what bottom-up processing addresses.
What is the difference between LGBTQ-affirming and trauma-informed therapy?
Affirming means your identity is safe in the room: no pathologizing, your language, no defending your existence. Trauma-informed means the clinician also has the training to work with the nervous system patterns underneath: the vigilance, the concealment fatigue, the internalized residue, the pacing and consent that a loaded system requires. Affirmation is the floor. Trauma competence is what produces change on it. Many people need to hear that the plateau they hit in affirming therapy was not their failure; it was the boundary of the method.
Can EMDR help with internalized homophobia or transphobia?
Yes. Internalized stigma typically formed early and is held somatically, which is EMDR's territory. Processing targets the formative material, the sermons, the jokes, the hallways, the silences, and drains the charge those installations still carry. Many clients find that shame which survived years of insight-oriented work finally shifts when the work moves to the level where it was stored.
Does this work over telehealth, and is that safe?
Yes on both counts. The somatic interventions translate fully to secure video, and many LGBTQ clients specifically prefer telehealth: your own space, your own privacy, no waiting room, and access to identity-competent care in regions where it is scarce. Sessions are protected by the same confidentiality as in-person work.
Do I have to disclose everything about my history for this to work?
No. Somatic processing does not require detailed narration, because the work targets the stored charge rather than the story, which is the point I make in why you don't have to tell your trauma story to heal. You share what you choose, at the pace your system sets. The processing happens either way.
Your Vigilance Made Sense. It Can Also Stand Down.
Every scan you have ever run had a reason. Every edit, every managed answer, every read of every room was your nervous system doing its one job with the information it had. Nothing about you was ever broken. You, friend, were guarded, and there is a difference.
Standing down is not something you can decide your way into. It is something the nervous system learns, one verified experience of safety at a time, and the experiences accumulate. But it stands down. Somewhere ahead of you is a parking lot you get out of without the scan, and a hand you take without doing the math. That is not naivety. That is what a settled system feels like, and it is buildable.
I work with LGBTQ adults in person at my Gulf Breeze, Florida office and online across New York, Florida, and all PsyPact states, using EMDR, Brainspotting, and CRM. You can see the areas I serve or request a 15-minute consultation.
The scan can become a choice again.
Explore More
Dr. Maria Niitepold, PsyD
EMDRIA-Trained Trauma & Somatic Therapist
Serving High-Achievers Across New York and Florida
(850) 696-7218. Call or text anytime.
Healing doesn't have to be hard. It just has to start.
(Disclaimer: This blog post is for educational purposes and does not constitute medical advice, a diagnosis, or a formal doctor-patient relationship. If you are experiencing a mental health crisis, please contact your local emergency services or call 988. LGBTQ young people can also reach The Trevor Project 24/7 at 1-866-488-7386.)


Comments